
How to Set Up a Starting Solids Feeding Schedule for Babies 6+ Months Old


The transition from a liquid-only diet to the introduction of solid foods is a significant developmental milestone for infants. As babies reach the six-month mark, their nutritional requirements begin to evolve, necessitating a strategic approach to feeding that balances breast milk or infant formula with the gradual introduction of nutrient-dense solids. Establishing a structured, yet flexible, feeding routine is essential for fostering healthy eating habits, supporting physical growth, and ensuring the baby develops the oral-motor skills required for independent feeding.

The Developmental Basis for Starting Solids
Pediatric nutrition guidelines generally recommend that infants begin solid food introduction around six months of age. At this juncture, developmental markers—such as the ability to sit upright with minimal support and the development of steady head control—signal that the infant’s digestive and neuromuscular systems are prepared for the transition.

During the initial phase (six to seven months), solids are intended to supplement, rather than replace, breast milk or formula. Pediatric dietitians emphasize that milk remains the primary source of nutrition at this stage, with most infants requiring approximately 28 to 32 ounces of milk daily. The primary objective of this phase is not caloric intake but rather sensory exploration and the development of swallowing and chewing mechanics.
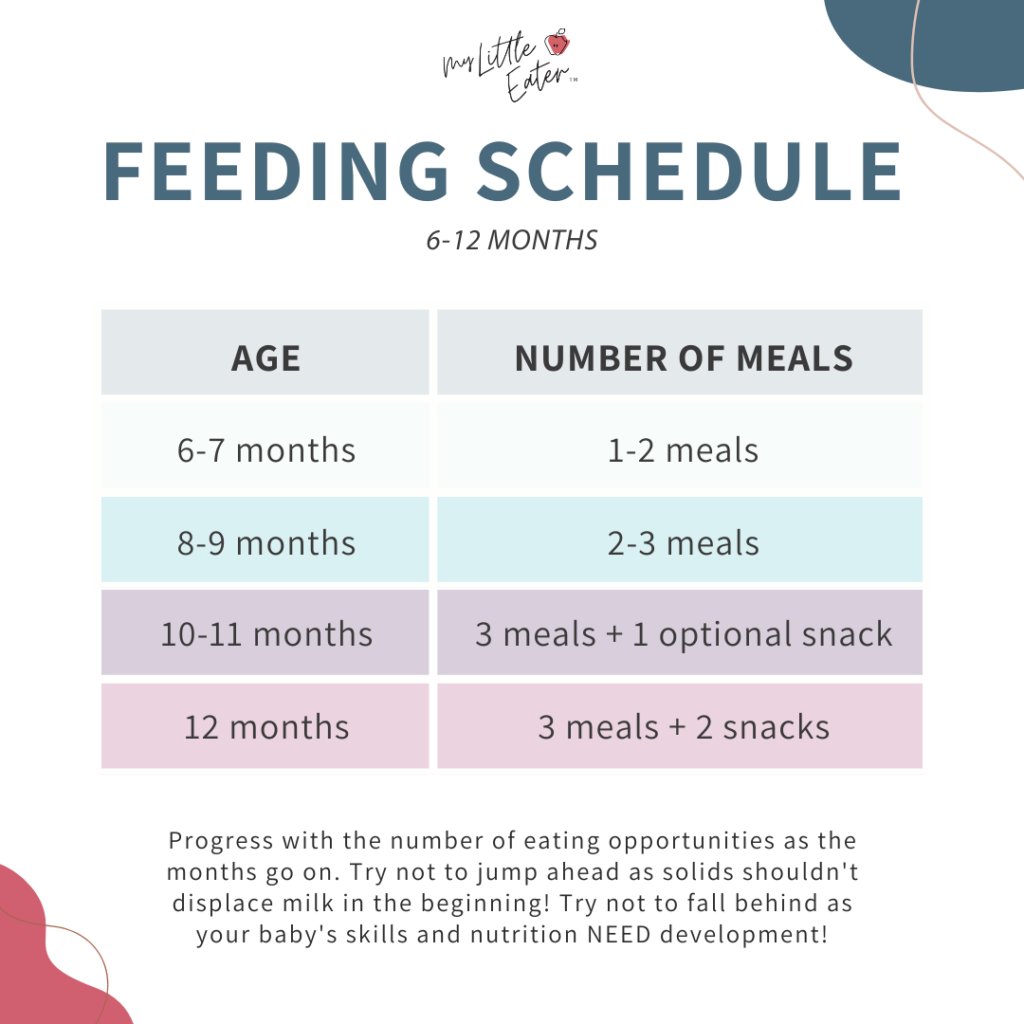
Chronology of Feeding Evolution (6–12 Months)
The progression of a child’s diet follows a predictable trajectory as they move toward their first birthday. By nine months, health experts suggest that infants should ideally be consuming three solid meals per day. This gradual increase in frequency is calibrated to match the infant’s decreasing reliance on milk.

- 6–7 Months: Infants typically consume five to six milk feedings daily, with one or two solid meals introduced 30 to 90 minutes after a milk feed. This spacing is critical to ensure the infant has enough appetite to engage with new textures without being so hungry that they become agitated.
- 8–9 Months: The feeding pattern shifts as the infant gains confidence. At this stage, milk feedings may decrease to four or five per day, totaling 24 to 32 ounces. The introduction of more complex food textures—often categorized as "Phase 3" in pediatric nutrition timelines—encourages chewing practice.
- 10–11 Months: Milk intake typically tapers to 18 to 24 ounces over three to four sessions. The diet becomes more diverse, incorporating modified family meals.
- 11–12 Months: As the child approaches the toddler threshold, solid meals become the foundation of their caloric intake. Milk requirements drop to 12 to 24 ounces, preparing the child for the transition to whole milk or alternatives at 12 months.
Managing Hunger Cues and Nutritional Balance
One of the most common challenges for parents is distinguishing between hunger and fatigue. Pediatric specialists underscore the importance of "responsive feeding"—the practice of recognizing an infant’s hunger and fullness cues to dictate the timing of meals.

If an infant consistently refuses solids, the issue is often related to the timing of the milk feed. Offering solids too soon after a bottle or nursing session leaves the infant satiated, while waiting too long can result in a "hangry" infant who lacks the focus required to learn new feeding skills. The recommendation of a 30-to-90-minute window between milk and solids is designed to strike a balance between satiety and readiness.

Data from the field of pediatric nutrition suggests that persistent, repetitive exposure to a variety of textures is essential for preventing picky eating behaviors later in childhood. When a child is allowed to touch, play with, and explore food, they are more likely to accept it. Conversely, skipping these developmental stages can hinder the acquisition of necessary oral-motor skills.

Implications of Transitioning to Toddlerhood
The transition to toddlerhood at 12 months marks a shift where solid foods become the primary source of nutrition. At this stage, there are no longer specific minimum milk requirements; in fact, excessive consumption of cow’s milk—often cited as exceeding 16 ounces per day—can lead to iron absorption issues and may suppress the child’s appetite for nutrient-rich solid foods.

Public health experts advise that, during this transition, milk should be served in a cup rather than a bottle. This change is not merely cosmetic; it encourages the child to consume milk as part of a meal rather than as a primary source of comfort or hydration, which can inadvertently lead to overconsumption.

Addressing Common Barriers
Parents often face logistical hurdles when implementing a schedule, particularly regarding work-life balance and the availability of time for morning meals. In scenarios where a parent is unavailable during the day, experts suggest that caregivers follow the same consistent feeding plan. If morning time is constrained, some families find success in moving the primary solid food introduction to the midday or evening, provided that the timing remains consistent to maintain the infant’s biological rhythm.

Safety remains the highest priority throughout this transition. Introducing "top allergens"—such as peanuts, eggs, or shellfish—should be done during the day when the parent is available to monitor the infant for any signs of an adverse reaction. This is particularly relevant for families with a history of food allergies or severe eczema, where consultation with a pediatrician is strongly advised before the introduction of high-risk foods.

The Role of Professional Guidance
The complexity of balancing nutritional needs with developmental milestones often necessitates professional guidance. Registered pediatric dietitians often serve as a bridge, providing frameworks that translate clinical recommendations into practical, actionable schedules.

The consensus among pediatric experts is that while a schedule is a vital tool, it should remain a living document. It must be adapted based on the infant’s growth spurts, teething, and changes in sleep patterns. Consistency is the key to stability, but rigidity should be avoided. If an infant is not meeting growth milestones or is consistently struggling with food intake, caregivers are encouraged to consult with a healthcare provider to rule out underlying medical or sensory issues.

Broader Public Health Impact
The approach to infant feeding in the first year of life has long-term implications for public health. By emphasizing diverse, whole-food options and establishing a routine that respects the child’s autonomy, parents can lay the groundwork for a lifetime of healthy eating. The prevention of early-onset picky eating and the reduction of excessive milk consumption in the second year of life are critical factors in addressing childhood obesity and nutritional deficiencies.

Ultimately, the goal of the 6-to-12-month feeding period is to transition the child from a dependent state to a position where they can participate in family meals with confidence. By providing a structured environment, caregivers allow the child to focus on the essential task of learning to eat, ensuring that they enter toddlerhood with the nutritional foundation necessary for optimal development. As the child continues to grow, the feeding schedule will naturally dissolve into the standard family meal routine, but the habits formed during this critical window will persist, underscoring the importance of a deliberate and informed approach to the start of solids.










